

Conditions: Obstructive Sleep Disordered Breathing (including Obstructive Sleep Apnea)
Obstructive sleep apnea is a dangerous but often unrecognized condition in which the upper airway collapses during sleep, briefly blocking breathing until a brief awakening restores airflow. This can occur in children as well as adults, although the causes and treatments differ between the two. Obstruction of the airway can occur hundreds of times a night, and each episode may last long enough to cause a drop in blood oxygen and an alarm-type response from the body, — including a surge of adrenaline, high blood pressure, and a fast or irregular heart rhythm—along with the loss of restful sleep. Some form of treatment is usually necessary.
diagnosing obstructive sleep disordered breathing

Sleep-disordered breathing is occurs when airflow is not free and easy during sleep. Sleep-disordered breathing progresses in severity from snoring, to upper airway resistance, and finally to obstructive sleep apnea. Obstructive sleep apnea is characterized by repeated episodes of complete or partial obstruction of the upper airway during sleep, despite ongoing effort to breathe, and is usually associated with a drop in blood oxygen saturation.
People with obstructive sleep apnea are rarely aware of their breathing difficulty, even upon awakening. The condition is often first noticed by others who observe the person during these episodes, or is suspected because of its effects on the body, most commonly excessive daytime sleepiness or decreased mental sharpness. The condition may be present for years without being identified, during which time the person may become accustomed to the daytime sleepiness and fatigue caused bysignificant sleep disruption. People who generally sleep alone are often unaware of the condition, lacking a regular bed-partner to notice and point out the signs. People with long-standing obstructive sleep apnea will often fall asleep briefly during the day when given an opportunity to sit or rest.
About Pediatric obstructive sleep apnea
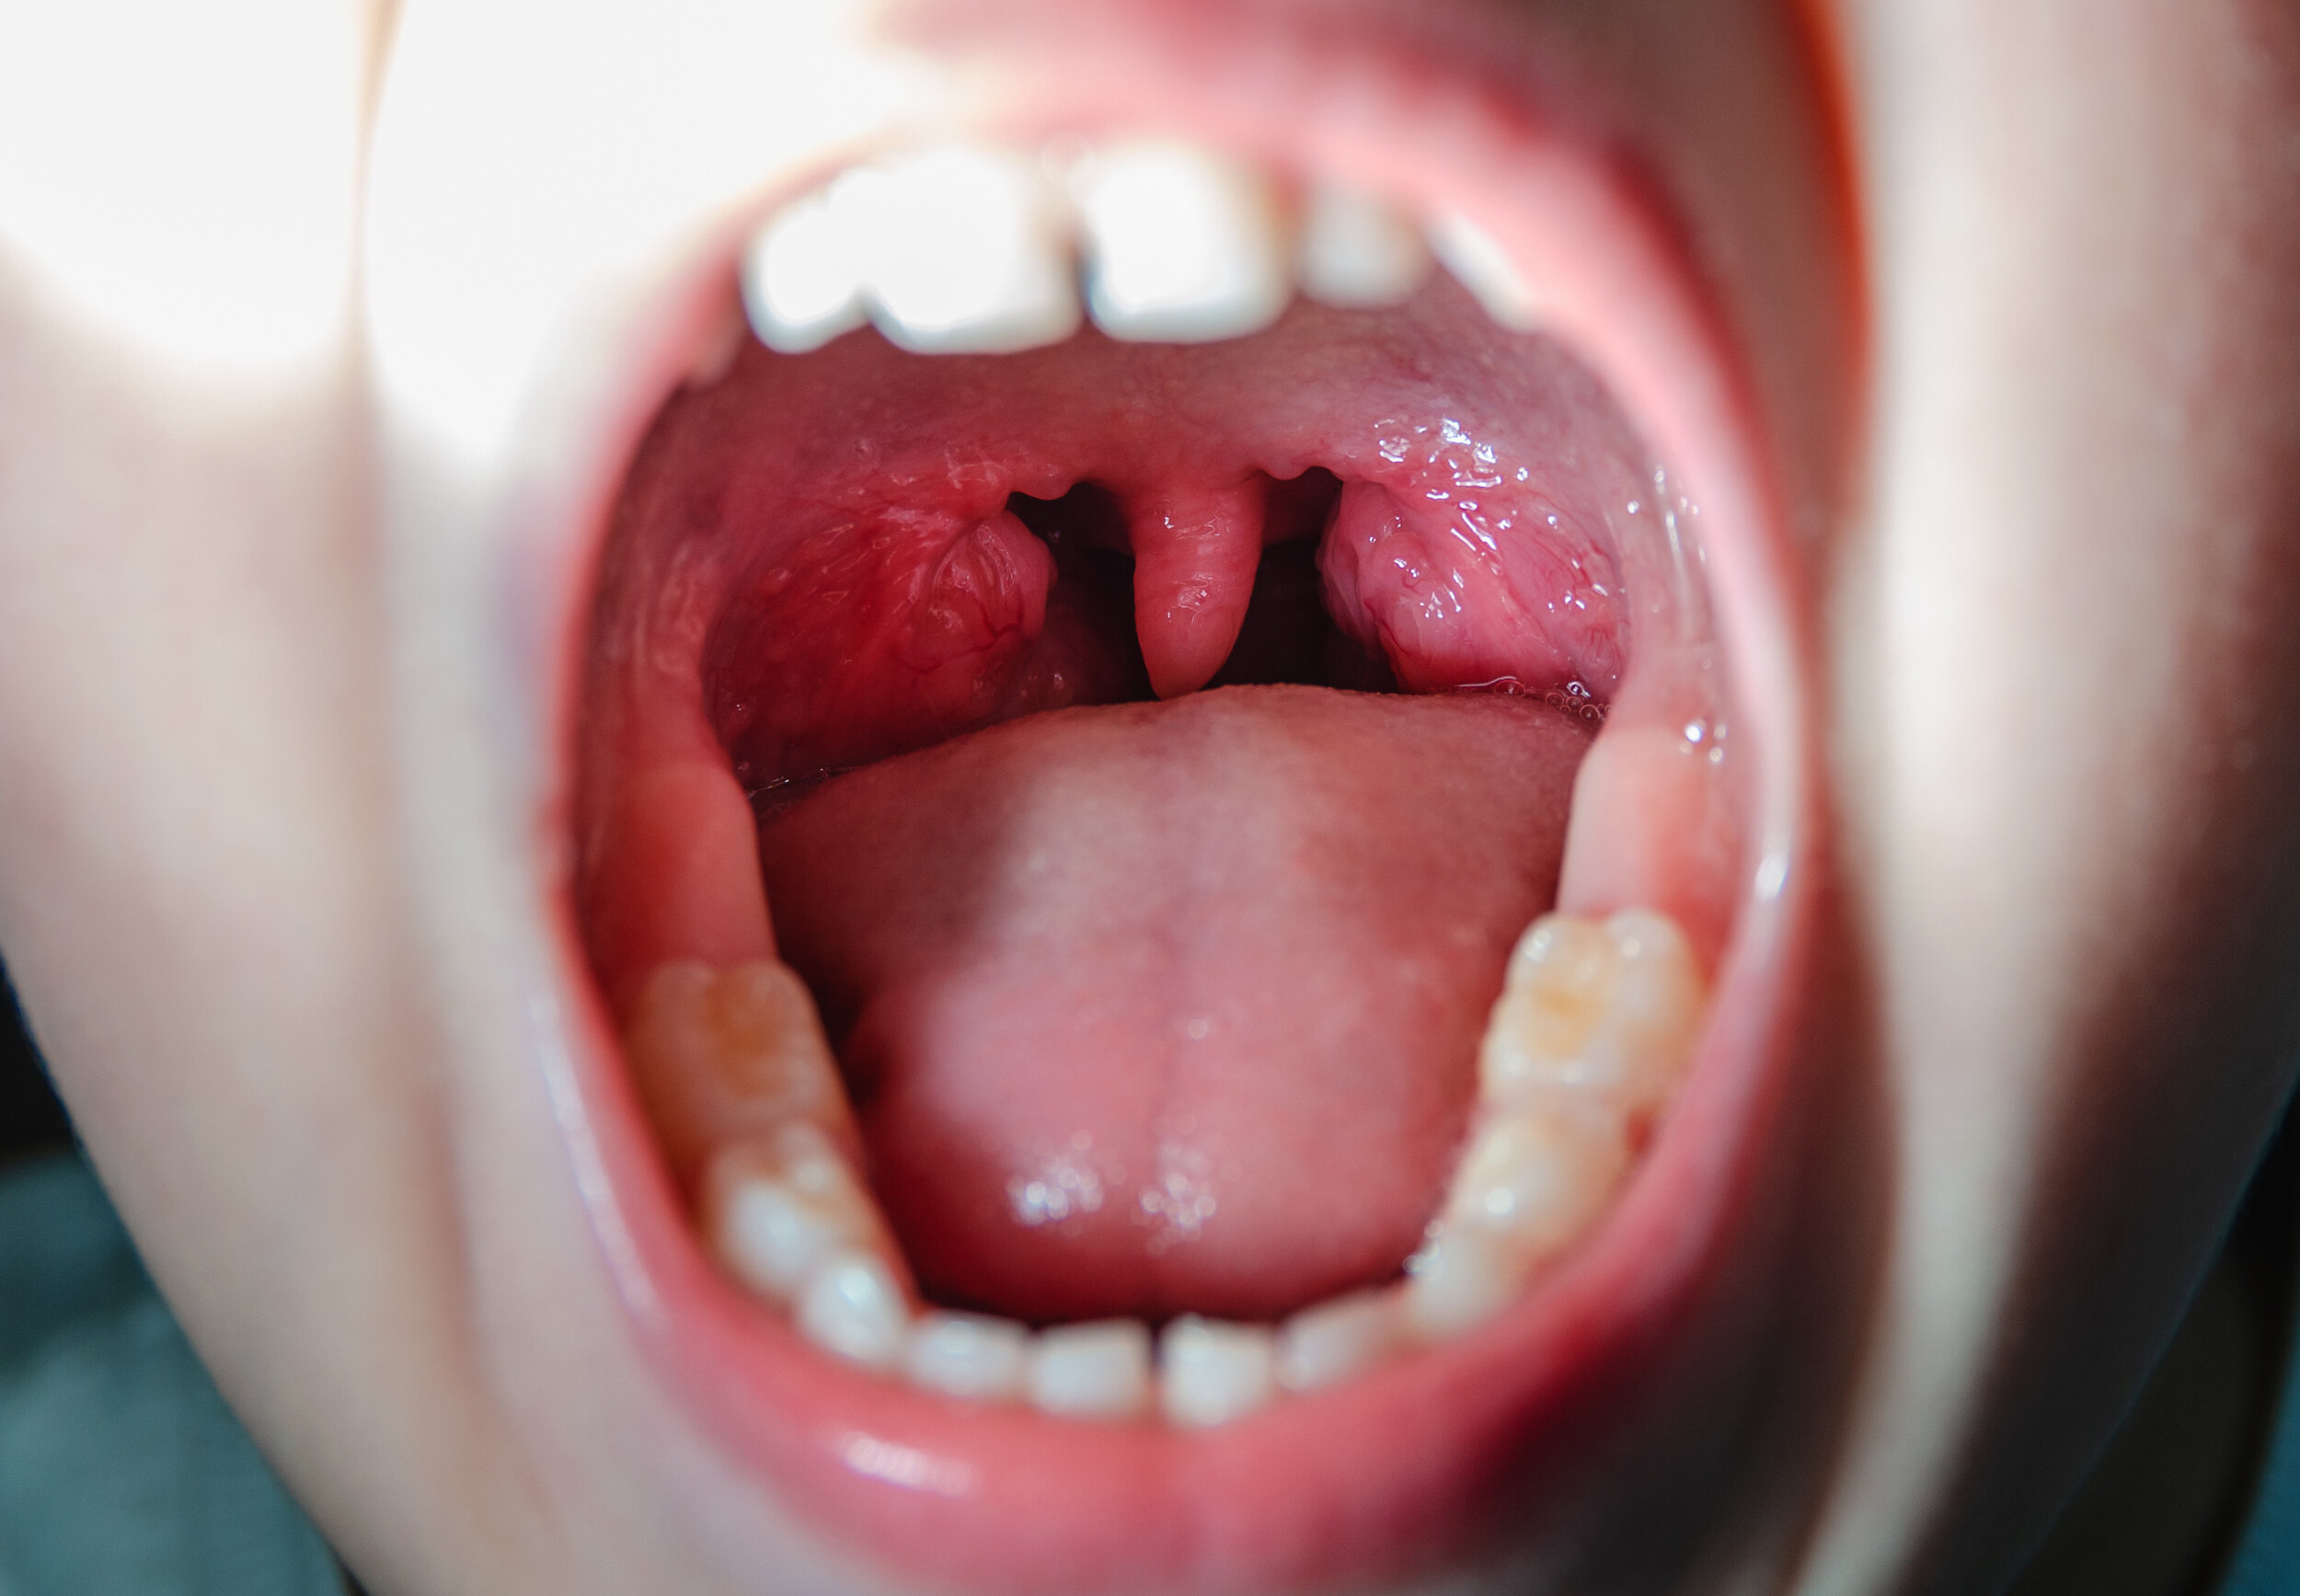
In children, especially those less than 8 years old, the predominant cause of obstructive sleep apnea is enlargement of the tonsils and adenoids. Childhood obesity and decreased muscle tone (such as in Down syndrome) are additional factors in some children. A parent's description of restricted or noisy breathing during sleep—along with bedwetting, morning headaches, aggressive behavior, and difficulty waking in the morning— may be enough to suggest the diagnosis. Paradoxically, many children with sleep-disordered breathing appear overactive and resist going to sleep. A sleep study is a more objective way to diagnose the condition, and is safe, but takes some time and effort. Untreated obstructive sleep apnea in children can lead to behavioral problems, stunted growth, and worse school performance.
about adult obstructive sleep apnea

In adults, obstructive sleep apnea tends to arise more from general crowding of the throat due to a large tongue, or soft palate, or obesity than from large tonsils or adenoids alone. During sleep, muscle tone decreases, allowing the throat to collapse more, and because consciousness is lost, airway blockage is not readily recognized or corrected. Factors that promote adult obstructive sleep apnea include aging (as the throat tissues relax and lengthen), obesity (adding to crowding of the throat airway), decreased muscle tone (such as from alcohol, sedating drugs, or neurologic problems), and brain injury. Diagnosis may be made clinically on the basis of a bed partner's description or by performing a sleep study. Untreated sleep apnea carries a significantly increased risk of death, heart attack, stroke, motor vehicle accidents, depression, and high blood pressure, among other conditions. Nasal airway obstruction contributes to increased airway resistance and may worsen obstructive sleep apnea.
Sleep study (polysomnogram)

Symptoms of sleep apnea usually include loud snoring, restless sleep, and excessive daytime sleepiness. A sleep study records several key measurements during a night of sleep. The gold standard, called the polysomnogram (PSG), is performed in a sleep lab room set up like a hotel room, and records many types of data (brain waves, eye movement, nasal and oral airflow, muscle tone, body position, chest and abdomen respiratory effort, a heart monitor, a blood oxygen monitor, and microphone over the windpipe) to give the most comprehensive and accurate picture. A sleep study performed in the sleep lab may be a split-night study, which also includes a trial of continuous positive airway pressure (CPAP) that may demonstrate correction of the sleep apnea and identify the lowest air pressure setting required for correction. Home Sleep Apnea Tests (HSATs) may be used in patients at least 18 years of age and measure only some of the data obtained from a PSG, specifically oxygen saturation, respiratory effort, and nasal airflow. HSATs are more convenient and are often more readily covered by insurance for initial testing than PSGs, but are less accurate and less informative.
fiberoptic exam of the throat (flexible laryngoscopy)

An effective method to assess the location of narrowing in the upper airway is to examine it with a small, flexible scope, which is passed through one nostril to the back of the throat. During this brief procedure, a maneuver to demonstrate collapsibility of the throat is performed, in which the mouth is closed, the nostrils are blocked, and the patient attempts to breathe in. The throat may collapse partially or fully, at the level of the soft palate or base of the tongue, and the narrowing may be circumferential or more in a single direction. The information gained from this Mueller maneuver indicates how successful a particular surgical technique may be. For example, if the soft palate collapses from front to back, a procedure to shorten the soft palate would likely be more effective than if the collapse were circumferential and lower in the throat. Because the Mueller maneuver is performed while awake and depends on how it is done, it does not always reflect how the airway behaves during actual sleep; for this reason, an examination performed under sedation (drug-induced sleep endoscopy) is increasingly used to help plan surgery.


This page