

Conditions of the Oral Cavity (Mouth): Labial Frenulum and Lingual Frenulum
Tongue tie and lip tie involve a restrictive band of tissue under the tongue or beneath the upper lip, and how they are diagnosed and what they cause are widely debated.

What are tongue tie and lip tie?
Tongue tie and lip tie are among the most talked-about topics in infant feeding and children's oral health today. They are also among the most debated. This page explains what these conditions are, how they are classified, how common they are, what problems they may or may not cause, and how they are evaluated, so that families can understand the terms and the ongoing scientific discussion behind them.
What is the normal anatomy and function of the frenulum?
A frenulum (plural: frenula) is a small fold of tissue lined by mucous membrane that connects one part of the mouth to another. Everyone has several of these normal structures. The two most discussed are:
The lingual frenulum, which runs along the midline from the floor of the mouth to the underside of the tongue. Rather than being a single discrete cord, it is better understood as a dynamic midline fold of tissue that becomes visible when the tongue is lifted. It helps stabilize the base of the tongue and normally does not prevent the tongue tip from moving. Its appearance ranges along a spectrum from thin and see-through to thicker and more opaque.
The maxillary labial frenulum (upper lip frenulum), which attaches the middle of the upper lip to the gum between the two upper front teeth. It is made mostly of connective tissue and helps provide stability for the upper lip.
Both of these are normal, near-universal structures that vary widely from person to person. Their presence alone is not abnormal.
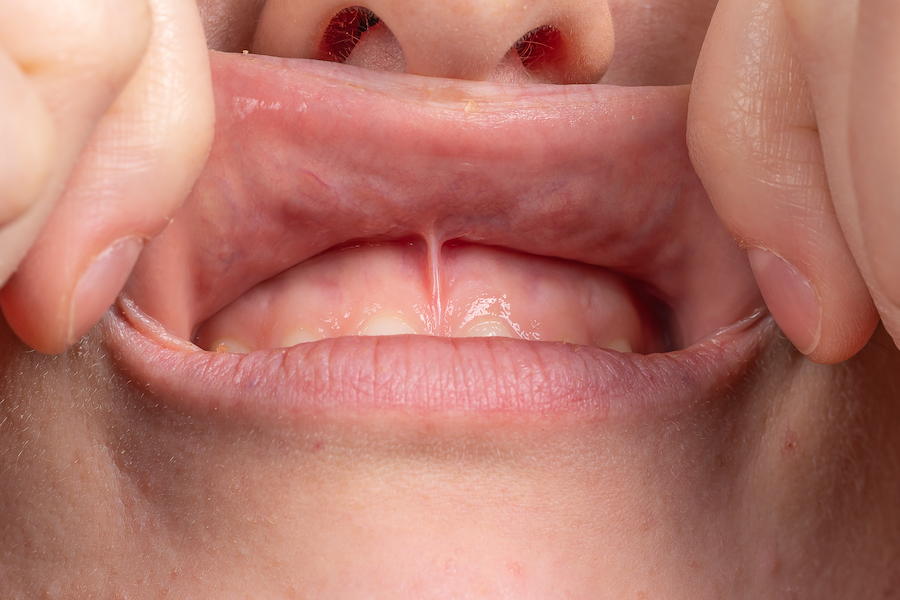
What defines a tongue tie and a lip tie?
Tongue tie (ankyloglossia), also called a shortened lingual frenulum, is best defined as a condition of limited tongue mobility caused by a restrictive lingual frenulum. The key word is mobility: a diagnosis rests on demonstrating that the tongue's movement is genuinely restricted and that the restriction can be traced to the frenulum, not simply on how the frenulum looks. Appearance alone does not establish the diagnosis.
Lip tie refers to an upper lip frenulum thought to be tight enough to restrict movement of the upper lip. This is a far less well-defined concept. Because the upper lip frenulum is a normal and highly variable structure (see lips), experts disagree about whether "lip tie" is a distinct condition at all, and some professional groups have suggested the term be retired.
How are these conditions classified?
There is no single, universally accepted classification system, and none of the existing systems has been formally validated. Several approaches are in use:
Anterior versus posterior: an "anterior" tongue tie describes a frenulum that extends to or near the tip of the tongue and restricts its movement. The term "posterior" tongue tie is far more controversial. Some clinicians use it for a frenulum attaching farther back or a tethering felt beneath the surface, while others argue that, based on the underlying anatomy, it is not a valid entity and the term should be abandoned.
Anatomy-based systems (such as the Coryllos classification and Kotlow grading) categorize the frenulum mainly by where it attaches, but do not assess how well the tongue actually functions.
Function-based systems (such as the Hazelbaker Assessment Tool for Lingual Frenulum Function and the Bristol Tongue Assessment Tool) attempt to score both the appearance and the movement of the tongue.
The lack of an agreed-upon, validated grading tool is one reason diagnosis varies so much from one practitioner to another.
How common are they, and is overdiagnosis a concern?
Reported rates of tongue tie vary widely, commonly cited between roughly 3% and 11% of newborns, with some studies reporting an even broader range depending on the criteria used. It is more often noted in boys.
What is striking is how sharply diagnosis has risen. In the United States, diagnoses of tongue tie and the number of frenulum-release procedures increased roughly tenfold over about fifteen years, with further increases afterward, and similar surges have been reported in Canada, Australia, New Zealand, and Denmark. Diagnoses have been more common among infants who are male, privately insured, and from higher-income areas.
This rapid increase has prompted concern that many children are being overdiagnosed and, in some cases, undergoing unnecessary procedures. Several factors likely contribute:
A widening of the definition to include less well-defined categories such as "posterior" tongue tie and lip tie
Greater emphasis on the benefits of breastfeeding and awareness that tongue tie can affect it
More lactation consultants, dentists, and other practitioners identifying and treating these conditions
Extensive social media and websites devoted to the topic
Whether the rise reflects a true increase, better detection, or overdiagnosis remains an open question, and experts explicitly acknowledge that in some communities overdiagnosis is occurring.
What problems may be associated with tongue tie and lip tie in infants?
Importantly, tongue tie is considered a variation of normal anatomy, and many affected infants and children feed, speak, and function without any difficulty. When problems do occur in infants, they may include:
Difficulty latching or staying latched during breastfeeding
Nipple pain for the mother
Reduced feeding efficiency, longer feeds, or inadequate milk transfer, sometimes affecting weight gain
These feeding difficulties are common in early infancy and have many possible causes. Tongue tie is only one potential contributor, and the same symptoms frequently arise from unrelated issues.
What problems may be associated with tongue tie and lip tie in older children and adults?
In older children and adults the evidence is weaker and more debated. Reported concerns include:
Difficulty with certain speech sounds
Mechanical limitations such as trouble licking the lips or keeping the teeth clean
A gap between the lower or upper front teeth
Difficulty with certain activities (for example, playing some wind instruments)
A sense of social self-consciousness
How is evaluation performed?
A careful evaluation focuses on function, not just appearance. For an infant, this typically includes:
A thorough history, including a detailed feeding and lactation history
A physical examination with both inspection and palpation (feeling) of the frenulum
Observation of the tongue's movement to determine whether mobility is genuinely restricted
Because breastfeeding difficulty is complex, a complete feeding assessment, ideally with lactation support, is considered a standard step before concluding that a frenulum is the cause. Other reasons for feeding trouble are also considered, such as nasal or airway obstruction, reflux, or craniofacial conditions like a cleft palate. Certain conditions (for example, a very small or set-back jaw, low muscle tone, neuromuscular disorders, or bleeding disorders) are important to identify because they change the picture.
What does the evidence show?
Tongue tie does not typically affect speech, and no definitive link has been established between the upper lip frenulum and a gap between the upper front teeth. What the evidence shows about release procedures is described on the lip and tongue tie treatments page.
What is the consensus viewpoint of the American Academy of Otolaryngology-Head and Neck Surgery?
The American Academy of Otolaryngology-Head and Neck Surgery (AAO-HNS) convened an expert panel whose statement reflected both agreement and genuine disagreement within the medical community. Its main points of consensus include:
Tongue tie (ankyloglossia) is best defined as limited tongue mobility caused by a restrictive lingual frenulum; a diagnosis made without demonstrated restriction of tongue movement is not supported by this definition.
The panel could not agree on the definition, or even the existence, of "posterior" tongue tie, and could not endorse a preferred grading system.
In some communities, children are being overdiagnosed with tongue tie and undergoing unnecessary surgery.
Tongue tie does not typically affect speech and does not cause sleep apnea.
The upper lip frenulum is a normal structure in infants, and its relationship to breastfeeding is unclear.
Management in brief
When and how a restrictive frenulum is released is described on the lip and tongue tie treatments page.

This page