

Learning Center: EAR PRESSURE
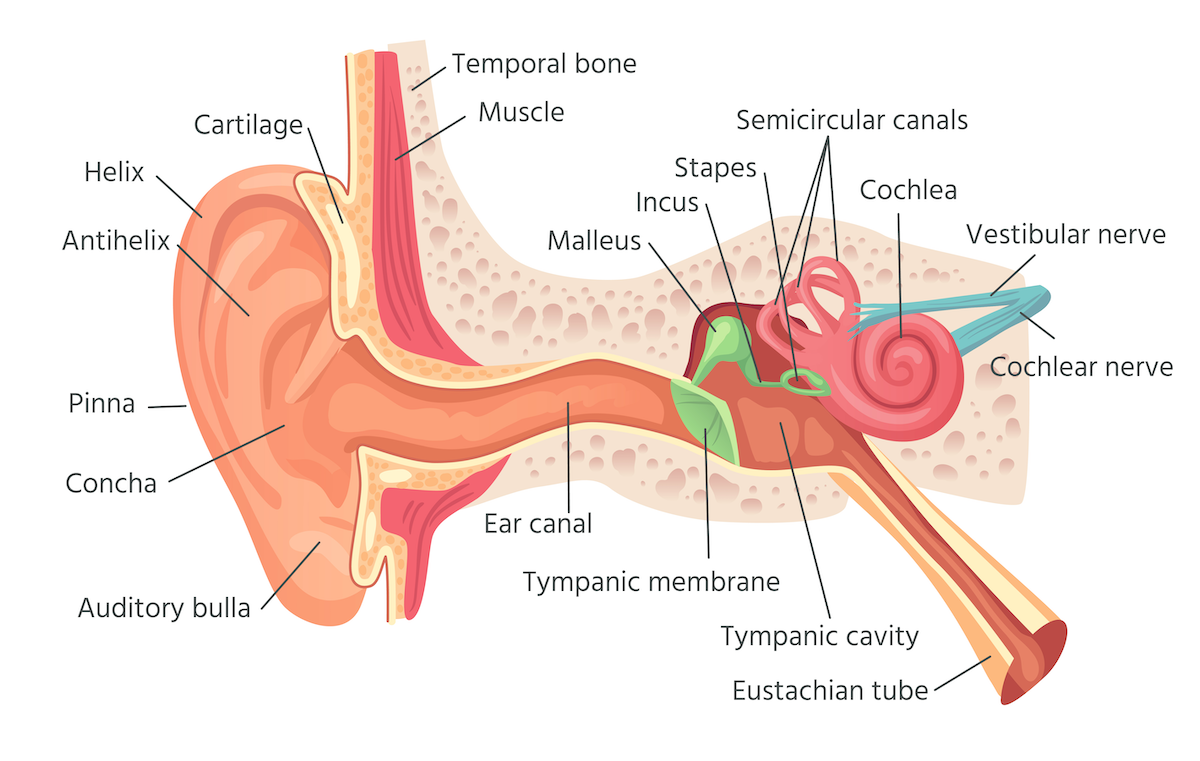
The Eustachian tube normally allows air pressure in the middle ear to adjust and equalize to pressure in the ear canal. A sense of ear pressure may or may not result from an actual pressure on the tympanic membrane.
EAR ANATOMY RELATED TO PRESSURE
Last reviewed: October 4, 2026
Introduction
A feeling of pressure, fullness or blockage in the ear is very common. Most often it comes from the Eustachian tube, the narrow passage that connects the middle ear to the back of the nose, not opening well enough to keep the air pressure behind the eardrum equal to the air pressure outside. This is called Eustachian tube dysfunction (ETD). It usually follows a cold, allergies or sinus inflammation and settles on its own within days to weeks. Ear pressure can also come from problems that have nothing to do with air pressure, including earwax, Meniere's disease, sudden hearing loss and jaw joint problems, so a persistent sense of fullness deserves an examination [1].
This page explains the anatomy behind ear pressure, how the Eustachian tube works, the types of ETD, other causes of ear fullness, and the evidence for treatments, including nasal sprays and balloon dilation. A numbered reference list is at the end of the page.
Anatomy
The air pressure in the ear canal is the pressure in the outside atmosphere. The pressure in the middle ear (labeled “tympanic cavity,” below) should equal the pressure in the ear canal or else the tympanic membrane with be pulled in or pushed out, causing stretch and discomfort. Unless the tympanic membrane is perforated, air egress from or inflow to the middle ear (tympanic cavity) is transmitted through the Eustachian tube, which opens at the throat (specifically, the nasopharynx).
The Eustachian tube is about 3.5 cm (1.5 inches) long in adults. The part nearest the ear is bone; the part nearest the throat is cartilage and soft tissue and is normally closed. It opens briefly when muscles of the palate contract during swallowing and yawning, letting a small amount of air into the middle ear. The lining of the middle ear slowly absorbs air, so without regular opening, pressure behind the eardrum falls, the eardrum is pulled inward, and over time fluid can collect (see ear fluid). In young children the tube is shorter, more horizontal and floppier, which is one reason ear infections and fluid are more common in childhood (see the ear infections page).
EUSTACIAN TUBE FUNCTION
Types of Eustachian tube dysfunction
An international consensus statement describes three types of ETD [1]:
Dilatory (obstructive) ETD: the tube does not open well. Symptoms are pressure or fullness, muffled hearing, popping or crackling, and discomfort, often worse after a cold or with allergies. Examination may show an eardrum that is pulled in or fluid behind it, and tympanometry may show negative pressure.
Barochallenge-induced ETD: the tube works well enough day to day but cannot keep up with rapid pressure changes, such as during the descent of an airplane or when diving. Symptoms occur only with those pressure changes.
Patulous ETD: the opposite problem, a tube that stays open. People hear their own voice and breathing loudly in the ear (autophony), and the symptoms often improve when lying down or bending forward. It can follow significant weight loss and is made worse by treatments meant for a blocked tube, so it is important to tell the two apart.
Other causes of ear pressure or fullness
A sense of ear fullness with a normal eardrum and normal pressure testing points away from ETD. Other causes include earwax, Meniere's disease (fullness with fluctuating hearing, tinnitus and attacks of vertigo) [2], sudden sensorineural hearing loss, which often first feels like a blocked ear and needs urgent treatment [3], temporomandibular joint (jaw joint) problems, and superior canal dehiscence, a thin spot in the bone over a balance canal that can cause fullness, autophony and dizziness with loud sounds or straining [4]. A blocked feeling in one ear that does not clear, especially in an adult with fluid behind the eardrum, should be examined, including a look at the back of the nose. See also the hearing, dizziness and tinnitus pages.
Evaluation
Evaluation includes a look at the eardrum, an examination of the nose and the back of the nose (often with a small scope), a hearing test (audiogram), and tympanometry to measure the pressure behind the eardrum. A short questionnaire, the ETDQ-7, is often used to measure symptoms. No single test confirms ETD, so the diagnosis combines the symptoms, the examination and the test results [1].
Treatment
Most ETD after a cold improves on its own. When it does not, options include [5, 6]:
Autoinflation: gently pushing air into the middle ear by blowing with the nose pinched and mouth closed (the Valsalva maneuver), or with a nasal balloon device.
Treating the nose: allergy control and treatment of sinus disease. Steroid nasal sprays are widely prescribed, but randomized trials have not shown that they relieve ETD on their own. A 2024 meta-analysis found no improvement in tympanometry compared with placebo or no treatment [7]. They are most reasonable when allergies or nasal inflammation are clearly present.
Decongestants: short-term use (no more than three days for sprays) can help around a flight or during a cold.
Ear tubes: a small tympanostomy tube placed in the eardrum bypasses the Eustachian tube and equalizes pressure directly. This is effective for persistent fluid and negative pressure, though it does not fix the tube itself.
Balloon dilation of the Eustachian tube: a small balloon is passed through the nose into the throat end of the tube and inflated for about two minutes, often in the office under local anesthesia. In the largest randomized trial, the tympanogram returned to normal at six weeks in 52% of patients after balloon dilation plus medical treatment compared with 14% with medical treatment alone, and symptom scores normalized in 56% versus 9% [8]. A second trial found symptom improvement lasting at least 12 months with no complications [9]. A 2025 Cochrane review concluded that balloon dilation may reduce symptoms over the first three months compared with non-surgical treatment, but rated the certainty of evidence as low, largely because many control patients crossed over to treatment [10]. A national consensus panel agreed balloon dilation is an option for adults with persistent dilatory ETD after medical treatment, not for patulous ETD [11].
More on treatment is on the Eustachian tube dysfunction treatment page.
Flying and diving
Pressure changes are greatest during an airplane's descent. Swallowing, yawning, chewing gum and gently equalizing with the Valsalva maneuver throughout descent help, and staying awake for landing makes this easier. People with a cold or allergy flare may benefit from a decongestant nasal spray about 30 minutes before descent. Infants can feed during descent. Severe pain, hearing loss, dizziness or drainage after a flight or dive can indicate barotrauma to the eardrum or inner ear and should be examined. People with repeated problems may be candidates for ear tubes or balloon dilation [1, 11].
Related pages on this site: Eustachian tube dysfunction, its treatment, ear fullness, ear fluid, ear infections and hearing.
Summary
Ear pressure usually comes from a Eustachian tube that is not opening well, most often after a cold or with allergies, and it often settles on its own [1].
Patulous ETD (a tube that stays open) causes loud hearing of one's own voice and is treated differently [1].
Fullness can also signal earwax, Meniere's disease, superior canal dehiscence or sudden hearing loss; sudden loss of hearing needs prompt evaluation [3, 4].
Steroid nasal sprays alone have not been shown to fix ETD in trials [7].
For persistent dilatory ETD, ear tubes and balloon dilation are options; balloon dilation improved symptoms and tympanograms in randomized trials, though the certainty of long-term evidence is low [8, 9, 10].
References
Schilder AG, Bhutta MF, Butler CC, et al. Eustachian tube dysfunction: consensus statement on definition, types, clinical presentation and diagnosis. Clin Otolaryngol. 2015;40(5):407-11. doi:10.1111/coa.12475 PubMed 26347263
Basura GJ, Adams ME, Monfared A, et al. Clinical Practice Guideline: Ménière's Disease. Otolaryngol Head Neck Surg. 2020;162(2_suppl):S1-S55. doi:10.1177/0194599820909438 PubMed 32267799
Chandrasekhar SS, Tsai Do BS, Schwartz SR, et al. Clinical Practice Guideline: Sudden Hearing Loss (Update). Otolaryngol Head Neck Surg. 2019;161(1_suppl):S1-S45. doi:10.1177/0194599819859885 PubMed 31369359
Ward BK, Carey JP, Minor LB. Superior Canal Dehiscence Syndrome: Lessons from the First 20 Years. Front Neurol. 2017;8:177. doi:10.3389/fneur.2017.00177 PubMed 28503164
Llewellyn A, Norman G, Harden M, et al. Interventions for adult Eustachian tube dysfunction: a systematic review. Health Technol Assess. 2014;18(46):1-180, v-vi. doi:10.3310/hta18460 PubMed 25029951
Mehta NK, Ma C, Nguyen SA, et al. Medical Management for Eustachian Tube Dysfunction in Adults: A Systematic Review and Meta-Analysis. Laryngoscope. 2022;132(4):849-856. doi:10.1002/lary.29878 PubMed 34606099
Nibhanupudy TJ, Patel A, Trinh CP, et al. Efficacy of intranasal corticosteroid sprays in relieving clinical signs of Eustachian tube dysfunction: a systematic review and meta-analysis of randomised, controlled trials. J Laryngol Otol. 2024;138(11):1065-1072. doi:10.1017/S0022215124000756 PubMed 38682673
Poe D, Anand V, Dean M, et al. Balloon dilation of the eustachian tube for dilatory dysfunction: A randomized controlled trial. Laryngoscope. 2018;128(5):1200-1206. doi:10.1002/lary.26827 PubMed 28940574
Meyer TA, O'Malley EM, Schlosser RJ, et al. A Randomized Controlled Trial of Balloon Dilation as a Treatment for Persistent Eustachian Tube Dysfunction With 1-Year Follow-Up. Otol Neurotol. 2018;39(7):894-902. doi:10.1097/MAO.0000000000001853 PubMed 29912819
Swords C, Smith ME, Patel A, et al. Balloon dilatation of the Eustachian tube for obstructive Eustachian tube dysfunction in adults. Cochrane Database Syst Rev. 2025;2(2):CD013429. doi:10.1002/14651858.CD013429.pub2 PubMed 40008607
Tucci DL, McCoul ED, Rosenfeld RM, et al. Clinical Consensus Statement: Balloon Dilation of the Eustachian Tube. Otolaryngol Head Neck Surg. 2019;161(1):6-17. doi:10.1177/0194599819848423 PubMed 31161864
Learning Center Main Index:
Throat:
swallowing, tonsils and adenoids, obstructive sleep apnea, voice, oral lesions and mucositis
Aesthetics:
skin regimen, injectables {neuromodulators (e.g., Botox), hyaluronic acid fillers (e.g., Juvederm), and others}, rhinoplasty, chin, facelift, neck lift, and brow lift, blepharoplasty (eyelid surgery), skin resurfacing, scar treatment
Tumors (benign and malignant/cancerous):
general tumor information, thyroid, parathyroid, skin, neck, lymphatics, oropharynx, larynx (voice box), salivary gland, nose and sinus, oral cavity (mouth and lips), nasopharynx, hypopharynx, radiation therapy, chemotherapy and immunotherapy, gastric feeding tube, central line
Nose and Sinus:
rhinoplasty (functional and cosmetic), sinusitis, breathing
Ear:

This page