

Learning Center: TONSILS AND ADENOIDS
Access information in greater detail.
Use the search tool or scroll down for your topic of interest.
ANATOMY OF THE TONSILS AND ADENOIDS
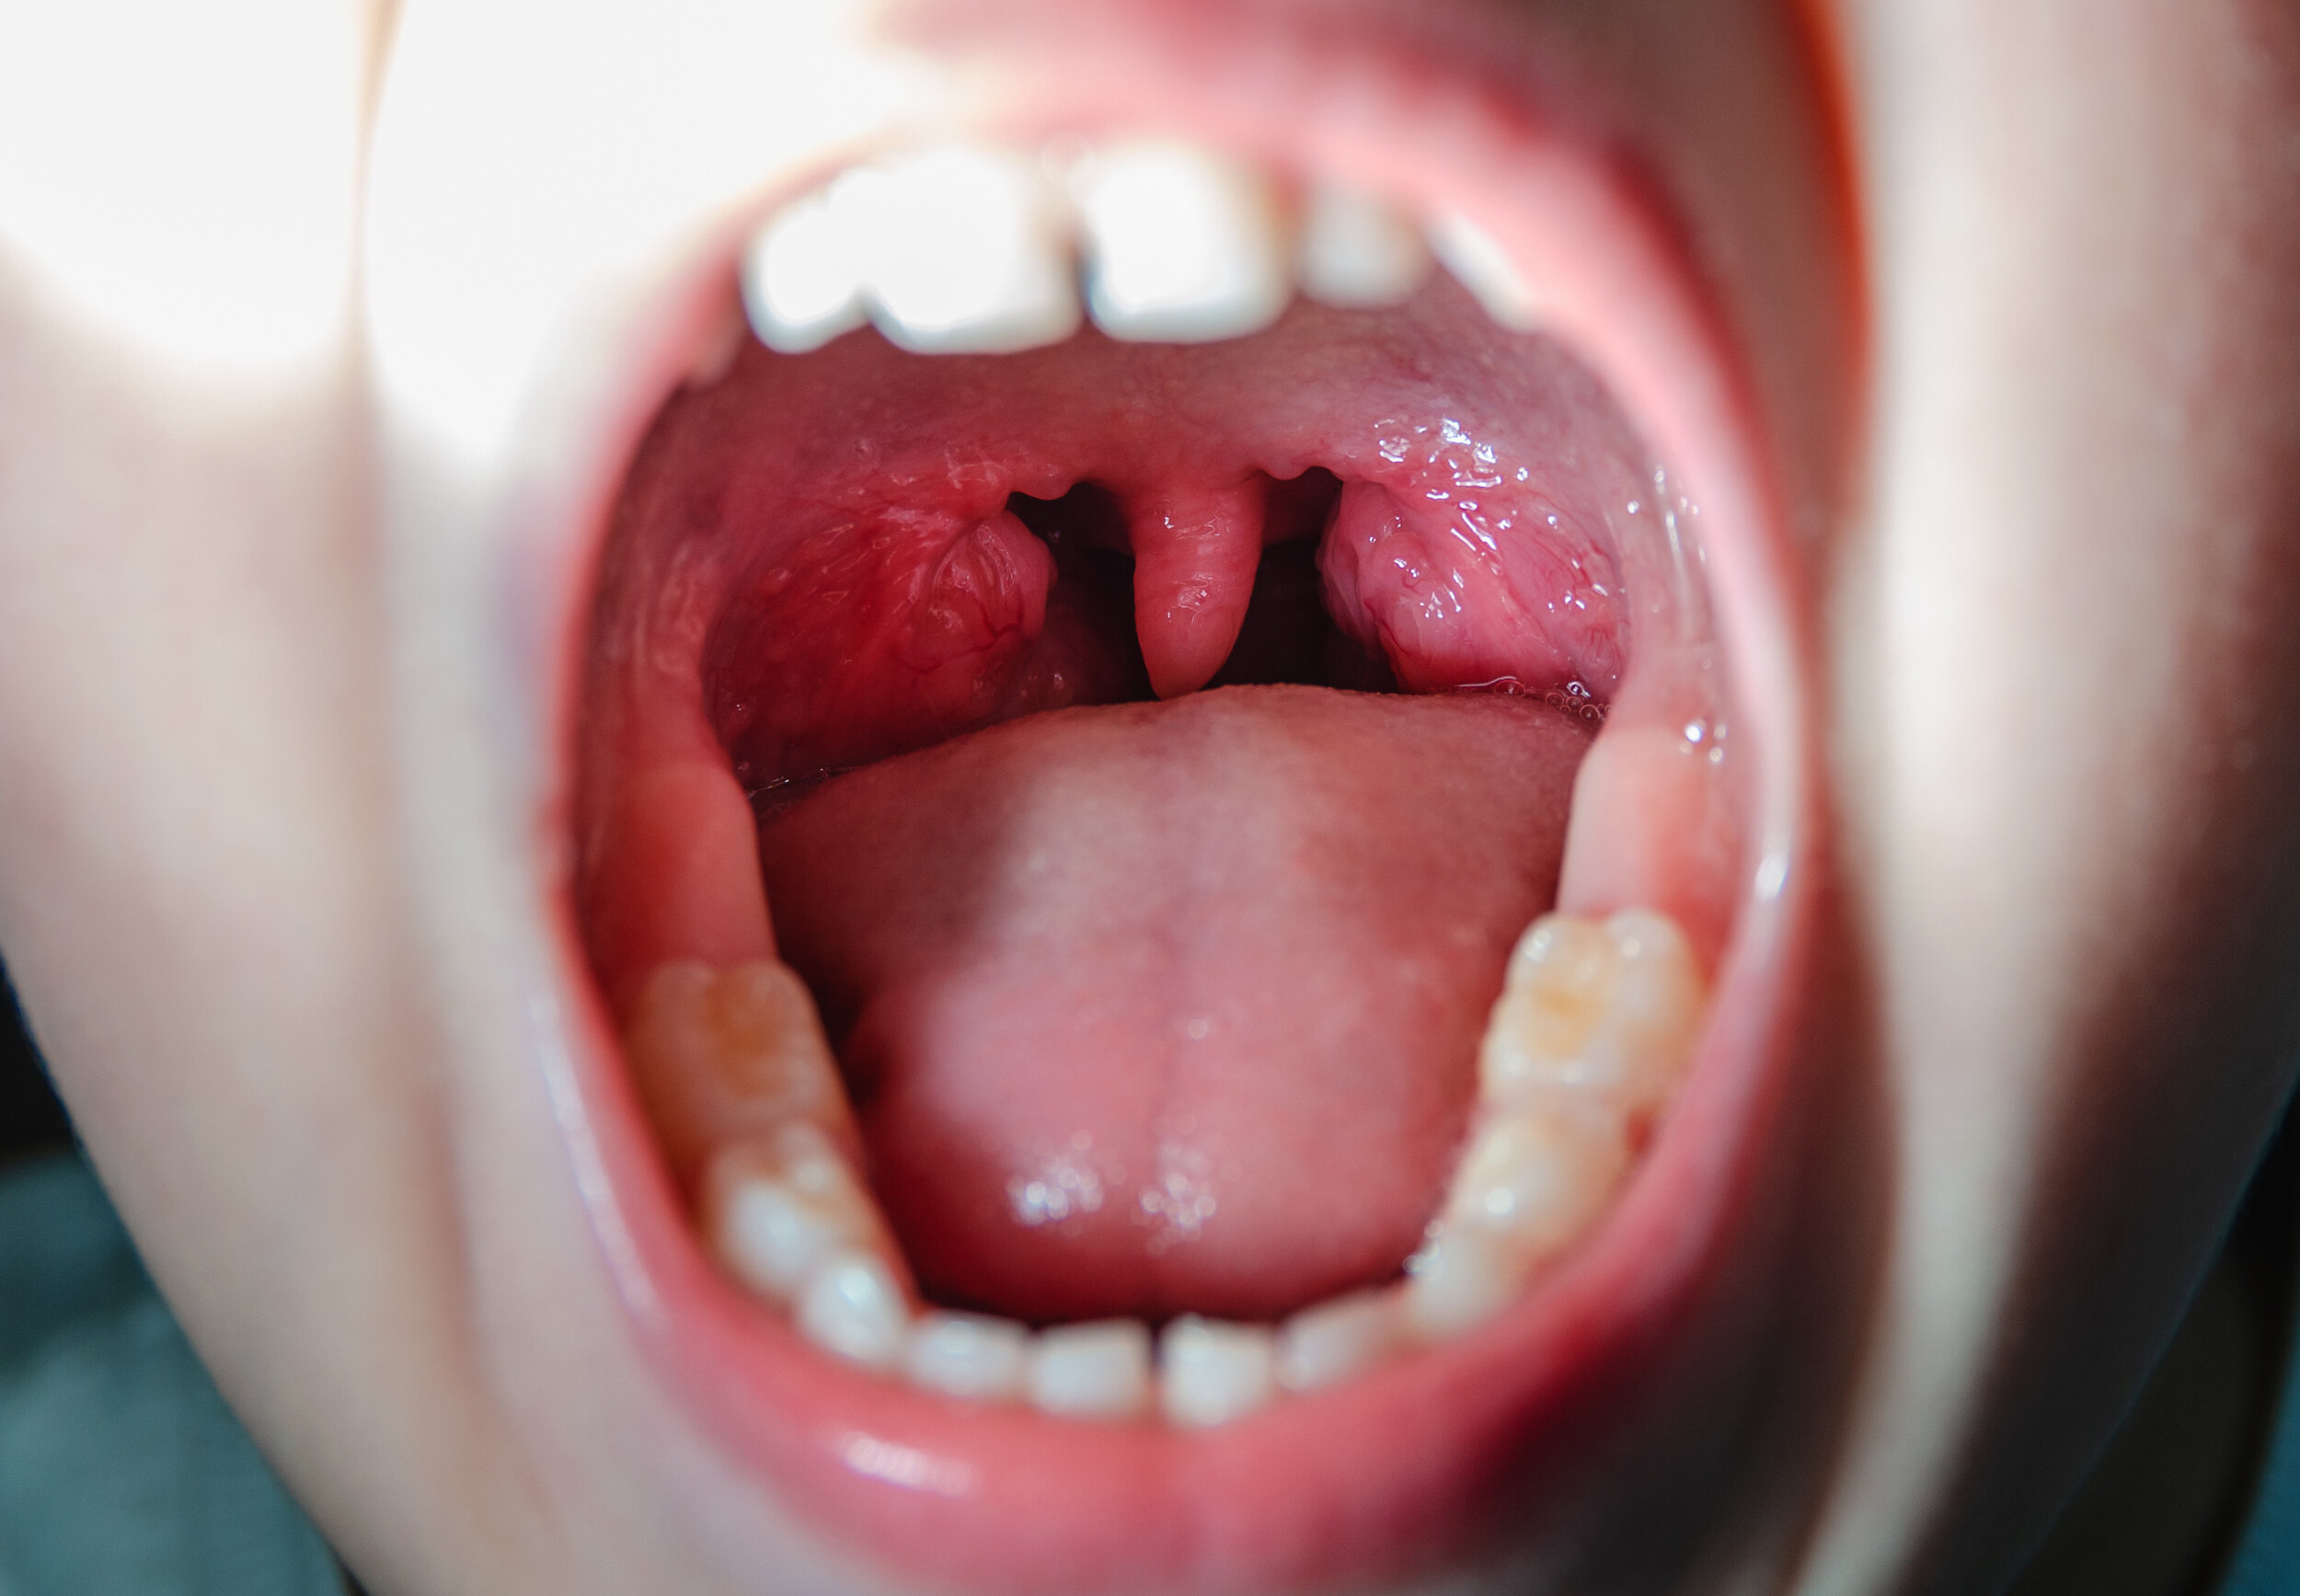
Large tonsils seen behind the tongue on the left and right.
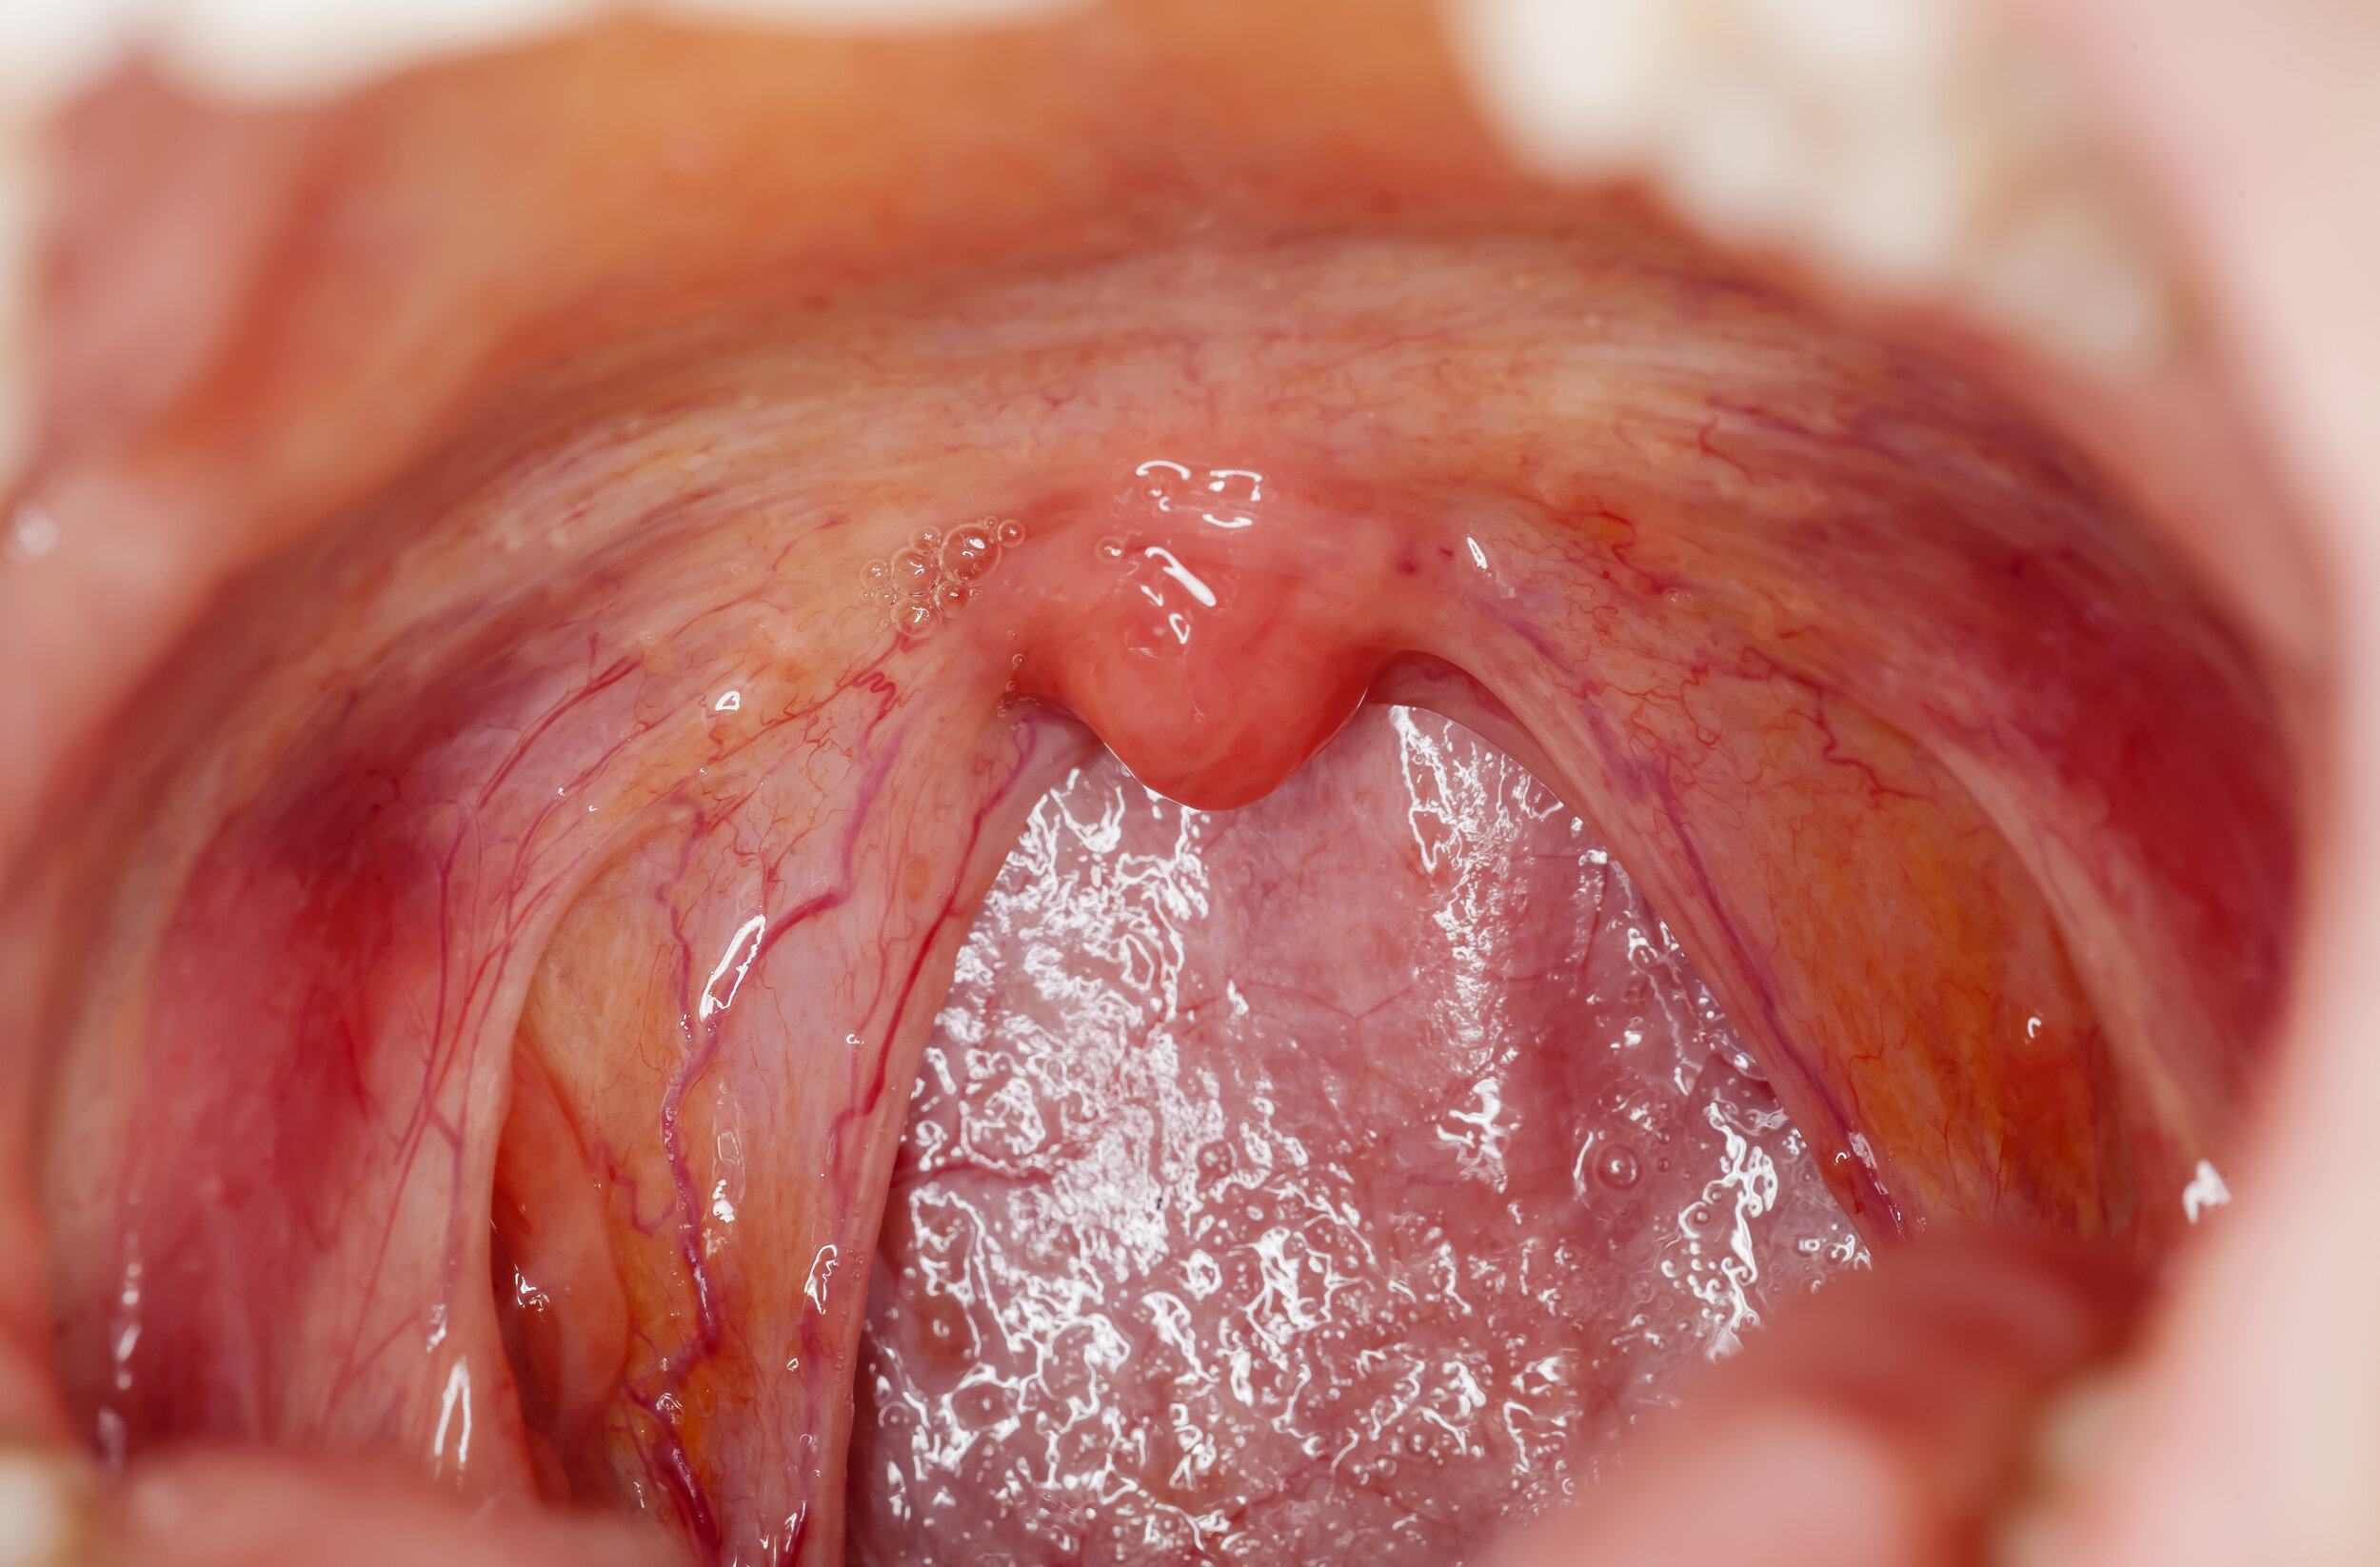
Minimal to no tonsil tissue present.

Adenoids are located at the “corner” between the back of the nose and the top of the throat.
FUNCTION OF THE TONSILS, ADENOIDS, and lingual tonsils
The tonsils, adenoids, and lingual tonsils are composed of lymphoepithelial tissue, which is rich in immune system cells, whose immune system purpose is complete early in life. To date, there are no studies that demonstrate a significant clinical impact of tonsillectomy or adenoidectomy on the immune system; minor changes in antibody (immunoglobulin) levels have been measured, but immune function remains adequate [1, 2]. One large Danish registry study did report somewhat higher long-term rates of some respiratory and allergic conditions after childhood tonsil or adenoid removal, although an observational study of this kind cannot show that the surgery caused them [3]. Tonsils, adenoids, and the lingual tonsils often cause health problems, with infections, airway blockage, or tumors.
Tonsillectomy for recurrent throat infections in children
Given the high numbers of throat infections and the number of tonsillectomies performed, a great deal of research has been devoted to indications for tonsillectomy in children, taking into account risks, benefits, and alternatives. Current guidelines are that the number of recurrent throat infections should be at least seven infections in the past year, at least five per year for two years, or at least three infections per year for the past three years [1]. Documentation for an episode should include a sore throat plus at least one of the following: temperature of at least 38.3°C (101°F), enlarged neck lymph node(s), discharge (exudate) on the tonsils, or a positive test for “strep” (group A beta-hemolytic streptococcus) [1]. Alternative indications for tonsillectomy, regardless of the numbers of throat infections include situations in which the child has had multiple antibiotic intolerances or allergies, “Periodic Fever, Aphthous Stomatitis, Pharyngitis, Adenitis” (PFAPA), which is a syndrome of repeated episodes of fever, mouth sores, sore throat, and swollen lymph nodes, or recurrent throat infections together with a history of a peritonsillar abscess [1, 4].
Tonsillectomy for Obstructive Sleep Disordered Breathing in Children
As with the above, good research has led to development of guidelines for tonsillectomy for obstructive sleep disordered breathing, which state that for children age two or older with large tonsils as well as some evidence of poor sleep (poor school performance, behavioral problems, growth retardation, or bed-wetting), tonsillectomy is a good option [1]. If the child is less than two years old or has a medical condition of Down syndrome, obesity, craniofacial abnormality, neuromuscular disease, sickle cell disease, or mucopolysaccharidosis, an overnight sleep study (polysomnogram) is indicated, before tonsillectomy is undertaken; if obstructive sleep apnea is diagnosed, tonsillectomy is recommended [1]. Tonsillectomy helps most normal-weight children with obstructive sleep disordered breathing [5, 6]. Tonsillectomy also helps overweight children with obstructive sleep disordered breathing but sleep is not always improved [7].
Other reasons for tonsillectomy
Chronic (long-lasting) tonsillitis, difficulty swallowing due to tonsils, and suspicion for tonsil cancer are reasons for tonsillectomy. Recurrent sore throats in adults do not have evidence-based guidelines as noted above for children, but the idea is the same. Randomized trials in adults now support this: in the largest, adults with recurrent tonsillitis who had tonsillectomy had about half as many sore-throat days over two years as those managed without surgery, at the cost of roughly two weeks of postoperative pain [8, 9]. Halitosis (bad breath) and tonsilloliths (tonsil stones) are possible reasons for tonsillectomy. Risks, benefits, alternatives and the expected outcomes should be discussed with your doctor prior to undertaking any procedure. Tonsillectomy is often considered after a second peritonsillar abscess, or after a single abscess in someone who also has frequent throat infections; most people do not have another abscess after the first one is drained, so a single abscess alone is not usually a reason for tonsillectomy [1].
WHEN AND WHY TO REMOVE ADENOIDS?
Adenoids are typically removed when:
The tonsils are being removed and the adenoid pad, inspected during the surgical procedure, is found to be enlarged.
A second set of pneumatic equalization ear tubes is being placed [10].
Adenoid enlargement is identified as a cause for nasal obstruction [10].
Adenoid infection is identified as a cause for chronic symptoms such as nasal discharge, including chronic rhinosinusitis in children [10, 11].
Considerations for tonsillectomy in children for obstructive sleep disordered breathing
Enlarged tonsils is the most common reason that children develop obstructive sleep disordered breathing.
Obstructive sleep disordered breathing is not solely due to enlarged tonsils; muscle tone also plays a role.
Obesity plays a major role in obstructive sleep disordered breathing [7].
A polysomnogram (sleep study done in the sleep lab) is considered the best test to confirm that the child has obstructive sleep apnea which would benefit from surgery [1].
A polysomnogram is not necessary in all cases and access may be limited by availability of sleep laboratories and willingness of insurers and third-party payers to cover the cost of testing. For an otherwise healthy child with a strong history of struggling to breathe with daytime symptoms of enlarged tonsils, a polysomnogram is typically not performed unless the parents want to confirm the diagnosis [1].
The success of tonsillectomy is variable. The age, weight, ethnicity, severity of obstructive sleep disordered breathing, and associate medical conditions all affect the success. Younger, normal weight, non-African-American children may have a resolution of obstructive sleep disordered breathing of about 80%; in the largest randomized trial, sleep study results normalized in 79% of children after surgery, compared with 46% with watchful waiting [5]. Rates of complete resolution are lower when stricter definitions of cure are used [6].
For obese children, tonsillectomy produces complete resolution of obstructive sleep disordered breathing < 50% of the time [7].
Caregivers need to be aware that their child may require additional interventions to cure his/her obstructive sleep disordered breathing which can vary from weight loss, medications, or wearing a special mask while sleeping that will keep the airway open. Some children may be candidates for more advanced sleep surgery procedures.
References
Mitchell RB, Archer SM, Ishman SL, et al. Clinical Practice Guideline: Tonsillectomy in Children (Update). Otolaryngol Head Neck Surg. 2019;160(1_suppl):S1-S42. doi:10.1177/0194599818801757 PubMed 30798778
Bitar MA, Dowli A, Mourad M. The effect of tonsillectomy on the immune system: A systematic review and meta-analysis. Int J Pediatr Otorhinolaryngol. 2015;79(8):1184-91. doi:10.1016/j.ijporl.2015.05.016 PubMed 26055199
Byars SG, Stearns SC, Boomsma JJ. Association of Long-Term Risk of Respiratory, Allergic, and Infectious Diseases With Removal of Adenoids and Tonsils in Childhood. JAMA Otolaryngol Head Neck Surg. 2018;144(7):594-603. doi:10.1001/jamaoto.2018.0614 PubMed 29879264
Burton MJ, Pollard AJ, Ramsden JD, et al. Tonsillectomy for periodic fever, aphthous stomatitis, pharyngitis and cervical adenitis syndrome (PFAPA). Cochrane Database Syst Rev. 2019;12(12):CD008669. doi:10.1002/14651858.CD008669.pub3 PubMed 31886897
Marcus CL, Moore RH, Rosen CL, et al. A randomized trial of adenotonsillectomy for childhood sleep apnea. N Engl J Med. 2013;368(25):2366-76. doi:10.1056/NEJMoa1215881 PubMed 23692173
Chinnadurai S, Jordan AK, Sathe NA, et al. Tonsillectomy for Obstructive Sleep-Disordered Breathing: A Meta-analysis. Pediatrics. 2017;139(2). doi:10.1542/peds.2016-3491 PubMed 28096514
Costa DJ, Mitchell R. Adenotonsillectomy for obstructive sleep apnea in obese children: a meta-analysis. Otolaryngol Head Neck Surg. 2009;140(4):455-60. doi:10.1016/j.otohns.2008.12.038 PubMed 19328330
Wilson JA, O'Hara J, Fouweather T, et al. Conservative management versus tonsillectomy in adults with recurrent acute tonsillitis in the UK (NATTINA): a multicentre, open-label, randomised controlled trial. Lancet. 2023;401(10393):2051-2059. doi:10.1016/S0140-6736(23)00519-6 PubMed 37209706
Koskenkorva T, Koivunen P, Koskela M, et al. Short-term outcomes of tonsillectomy in adult patients with recurrent pharyngitis: a randomized controlled trial. CMAJ. 2013;185(8):E331-6. doi:10.1503/cmaj.121852 PubMed 23549975
Rosenfeld RM, Tunkel DE, Schwartz SR, et al. Clinical Practice Guideline: Tympanostomy Tubes in Children (Update). Otolaryngol Head Neck Surg. 2022;166(1_suppl):S1-S55. doi:10.1177/01945998211065662 PubMed 35138954
Brietzke SE, Shin JJ, Choi S, et al. Clinical consensus statement: pediatric chronic rhinosinusitis. Otolaryngol Head Neck Surg. 2014;151(4):542-53. doi:10.1177/0194599814549302 PubMed 25274375
Last reviewed: October 4, 2026.
Additional links
Learning Center Main Index:
Throat:
swallowing, tonsils and adenoids, obstructive sleep apnea, voice, oral lesions and mucositis
Aesthetics:
skin regimen, injectables {neuromodulators (e.g., Botox), hyaluronic acid fillers (e.g., Juvederm), and others}, rhinoplasty, chin, facelift, neck lift, and brow lift, blepharoplasty (eyelid surgery), skin resurfacing, scar treatment
Tumors (benign and malignant/cancerous):
general tumor information, thyroid, parathyroid, skin, neck, lymphatics, oropharynx, larynx (voice box), salivary gland, nose and sinus, oral cavity (mouth and lips), nasopharynx, hypopharynx, radiation therapy, chemotherapy and immunotherapy, gastric feeding tube, central line
Nose and Sinus:
rhinoplasty (functional and cosmetic), sinusitis, breathing
Ear:

This page